This is an excerpt from Second Opinion, a weekly analysis of health and medical science news emailed to subscribers Saturday mornings. If you haven’t subscribed yet, you can do that by clicking here.
Scroll through social media as a woman of a certain age and you might spot a trend.
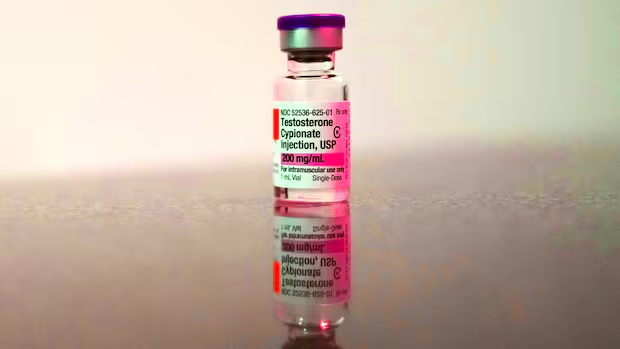
Testosterone is being touted as a cure-all for menopause symptoms — everything from a sluggish sex drive to night sweats — by a range of influencers and physicians.
While the hormone isn’t approved to treat menopause symptoms in Canada or the U.S., more women are using it off-label. And policymakers are taking note.
In mid-September, American regulators started evaluating testosterone therapy for menopausal women and called on drugmakers to do more women-specific research.
“Women deserve to have testosterone options that are formulated and dosed specifically for them,” said Dr. Dorothy Fink, deputy director of the Eunice Kennedy Shriver National Institute of Child Health and Human Development, at a live-streamed workshop on Sept. 17.
But is there solid science to back up the use of testosterone to treat menopause? Not quite yet, and certainly not for every single woman, multiple menopause researchers told CBC News.
The debate over testosterone is happening against a complex backdrop, as menopausal hormone therapy in all its forms is moving mainstream after years of declining use.
“In the past, a lot of the fear around hormone therapy was really not based on evidence,” said Dr. Marie Christakis, a gynecologist and researcher at Weston and O’Born Centre for Mature Women’s Health at Mount Sinai Hospital in Toronto.
“And now a lot of the salesmanship of hormone therapy is also not based on evidence.”
Years of caution around hormone therapy
Menopause, in the simplest terms, is when a woman’s periods end for good.
The transition time before is marked by dramatic changes in hormone levels, leading many women to experience a range of symptoms: hot flashes, insomnia, vaginal dryness, to name a few.
For some women, it’s unpleasant. For others, it can be debilitating.
Traditional hormone therapy is meant to combat those health impacts, including estrogen-only menopause therapy and combined estrogen and progesterone, which both come in multiple forms: pills, vaginal creams and skin patches.
But there’s no one-size-fits-all approach to hormone therapy.
The 2002 publication of a major U.S. clinical trial on conventional menopause treatments was a flashpoint, as it appeared to show that any benefits from combined estrogen-progesterone hormone therapy didn’t outweigh higher risks it carried of breast cancer, heart disease and stroke.
Further research uncovered methodological flaws in the initial study, which focused on older, post-menopausal women, skewing their overall risk of cancer and heart issues. Yet the fears around hormone therapy persisted, and use dropped as a result.
But the tides have turned.
In 2021, the Journal of Obstetrics and Gynaecology issued a guideline indicating that menopausal hormone therapy is the “most effective option” for women to manage symptoms like hot flashes, noting it can be safely used for most women under 60 or who are less than 10 years post-menopause.
Just last year, U.S. officials removed longstanding “black box” warnings about potential risks of cardiovascular disease, stroke, breast cancer and dementia linked to menopause hormone therapies — a move backed by the Society of Obstetricians and Gynaecologists of Canada.
There are now more approved, accessible options to manage the transition into menopause.
But the question many women are now facing is, should testosterone be one of them?
Testosterone not part of ‘true regime’ for menopause care
Testosterone — a sex hormone — is produced at lower levels in women than in men, and gradually declines with age, typically long before the point of menopause.
“The evidence is actually that testosterone levels in pre-menopausal women decrease sometime in the early to mid-thirties,” said clinician-scientist Dr. Jerrilyn Prior, a professor emerita of endocrinology and medicine at the University of British Columbia.
There’s actually no physiological reason for menopausal women to take testosterone in general, she said, since unlike the sharp drops in the production of estrogen and progesterone, a woman’s ovaries continue producing steadily-lower levels of testosterone for years.
“The only situation in which testosterone I think is necessary, and very helpful, is someone who’s had their ovaries removed,” Prior said.
“They don’t have that natural testosterone production anymore.”
WATCH | How a Vancouver clinic is helping women with severe menopause symptoms:
Vancouver menopause clinic seeks to help those with severe symptoms
Some doctors in Vancouver say help is available for those with severe menopause symptoms. The Complex Menopause Clinic at B.C Women’s Hospital has been open since January 2025, and seen more than 1,000 patients across the province. The CBC’s Johna Baylon visits the clinic to see how it has helped people deal with the onset of menopause.
The hormone has never really been part of the “true regime” of therapy options for menopause-related symptoms, said Dr. Shafeena Premji, founder and medical director of the Milestone Menopause Centre of Southern Alberta and a board member of the Canadian Menopause Society.
Most research on testosterone and menopause is primarily focused on post-menopausal women who have hypoactive sexual desire disorder, she said.
“This is where a woman has low desire that is causing personal distress,” Premji said, explaining how a major drop in libido can be linked to a range of health issues beyond hormones, from other medical conditions to medication side effects and mood disorders.
Body image concerns and life stressors can also play a role, she said, which means treating the condition often requires a thoughtful approach beyond just hormone therapy.
The challenge is that modern women are now bombarded with “misinformation and misguidance” about how to manage menopause, Premji said.
“We can’t make false claims and promise things to women when we don’t actually have the research to back that up.”
WATCH | New Winnipeg menopause clinic opens its doors:
New menopause clinic will address gaps in care: Winnipeg doctor
The Manitoba government is touting the planned 2027 opening of a specialized menopause clinic that will restore services lost when the Mature Women’s Centre closed in 2017. Meanwhile, Tory Leader Obby Khan doubts the province will be able to expand the Port of Churchill and build a pipeline within four years, which is reportedly what the prime minister wants.
Concern over risks, lack of safety data in women
Amid their ongoing assessment of testosterone’s benefits and risks for women, American regulators are requesting public feedback into mid-October, though the evaluation process could last far longer than that.
But as it stands, there’s insufficient data to recommend testosterone for broader issues linked to mood, cognition or general well-being, said Rajita Patil, director of the UCLA Comprehensive Menopause Care Program, at the U.S. Food and Drug Administration’s September workshop held.
She spoke about how oral testosterone is also not recommended because of unfavourable effects on cholesterol levels. Multiple experts also stressed there’s concern about broader risks, a lack of long-term safety data in women and the potential for unwanted physical side effects.
“With testosterone, there’s a very fine line between [potential benefits and] starting to get hair where you don’t want it, and oily skin, and having to wash your hair every two days or something,” Prior told CBC News.
Not every symptom linked to menopause
Women living with menopause should consider getting a full health assessment from a medical professional, Premji said, since aging bodies experience a range of health impacts beyond just changing hormones.
“Not every symptom is always related to perimenopause,” she said, referring to the years-long transition phase before menopause hits.
“We have to be able to screen for other medical conditions that could be contributing to symptoms before we attribute everything to menopause.”
Despite the buzz and promises of testosterone therapy, Prior also stressed that menopause itself isn’t a disease or something that has to be fixed.
She said anyone selling an understudied treatment might just have “something to gain.”